Midway through the run, your knee gave way. The MRI scan now reveals the words that no athlete, and no defence aspirant, wants to see: ACL tear. Your doctor may have mentioned ACL reconstruction surgery. Now your mind is likely racing with questions about pain, cost, how soon you can walk again, and if you are preparing for the Services Selection Board (SSB), one question that matters just as much: will this knee still get you through your medical?
I completely get why you’re worried. I’ve assisted numerous patients with this identical procedure at my clinic, Dr. Prince Uchadiya Orthopaedic Joint Care Clinic in Indore, and a good number of them were NDA, CDS and AFCAT aspirants who came to me specifically because of the SSB medical ahead of them. I am Dr. Prince Uchadiya, and I explain the entire process in simple terms, including how it connects to your SSB medical fitness, so you know exactly what to expect.
Key Takeaways
- The ACL tears in over 200,000 people each year in the US alone. It is one of the most common sports injuries seen by joint surgeons (AAOS data).
- ACL reconstruction gives a good outcome in 75% to 97% of patients, per published medical research (a clinical review).
- Rushing recovery often backfires. Returning to sport, or appearing for your SSB medical, before the knee has fully stabilised carries a real risk of reinjury or a poor assessment.
- Most patients are up and walking with assistance within 24 to 48 hours and are started on physical therapy almost immediately post-surgery.
- Meniscus tears are common with ACL injury and often can be repaired at the same surgery.
- A history of ACL reconstruction does not automatically mean permanent rejection at the SSB medical. The outcome depends on functional stability, time since surgery and how the case is presented to the medical board.
What Is ACL Reconstruction Surgery?
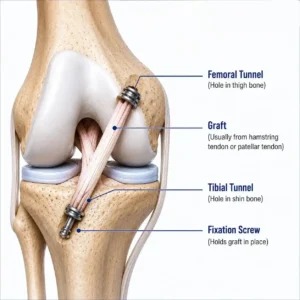
The ACL, or anterior cruciate ligament, is a band of tissue deep inside your knee. It prevents your shinbone from moving forward under your thighbone. A severe twist, a harsh landing or a direct hit while playing sports or during physical training might rupture it.
An ACL injury won’t heal on its own. There’s very little blood supply to the area, so the body isn’t able to mend it the way it would a sprain.
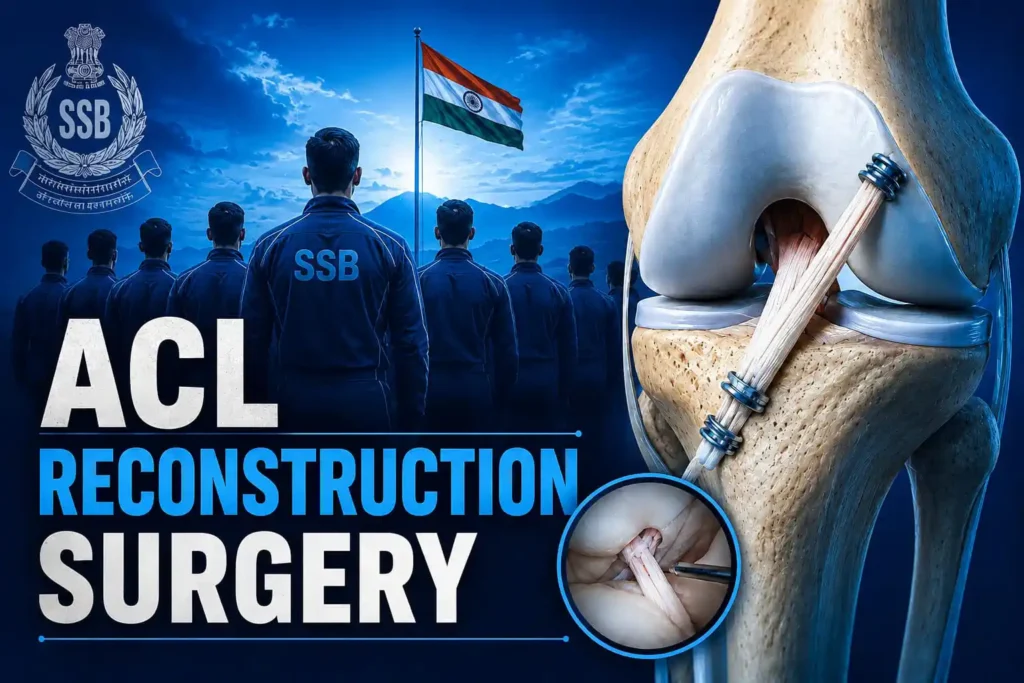
This surgery involves replacing the damaged ligament with a fresh graft. The graft is normally taken from your own body or from a donor tissue bank. The objective is clear: to restore a knee that can bear weight, twist, pivot and be relied upon again, whether that is on a football field or during your physical efficiency test.
When Do You Actually Need This Surgery?
Not every ACL tear needs surgery. I suggest ACL reconstruction mainly for athletes, active young adults and anyone whose knee keeps giving way during normal movement.
If you sit at a desk all day and rarely play sports, guided rehab alone may work well. But for pivoting sports like football, basketball or badminton, and for the running, obstacle courses and drills that defence training demands, a loose knee often leads to more cartilage damage over time.
Age matters less than people think. I have operated on teens and on patients past 50. The real factor is always activity level, not age, and few activity levels are as demanding as the ones the armed forces expect of you.
“I always tell my patients, the choice to operate should match your lifestyle, not just your MRI report. A 45-year-old badminton player and a 45-year-old desk worker with the same tear may need very different plans,” says Dr. Prince Uchadiya.
How Long Does the Procedure Take?
A standard ACL reconstruction takes about 60 to 90 minutes in the operating room. If we also fix a torn meniscus at the same time, it may take a bit longer, closer to 90 to 120 minutes.
The surgery is done under spinal or general anaesthesia. You will feel nothing during the surgery. Most patients go home the next day.
The ACL Reconstruction Surgery Procedure
Diagnosis and Pre-Surgery Planning
Before surgery, we confirm the tear with a physical exam and an MRI. One reliable check is the Lachman test. It shows how much the knee shifts out of place, the same kind of stability check a medical board will look for later.
We also check your general health and any other knee damage. Then we plan the surgery around your goals. If you play a specific sport, we factor that into the graft choice and the rehab plan, since a runner and a wrestler recover in slightly different ways. If your goal is to clear an SSB medical, tell your surgeon upfront. It changes how we time your rehab milestones and what documentation we prepare for your board.
Choosing the Right Graft
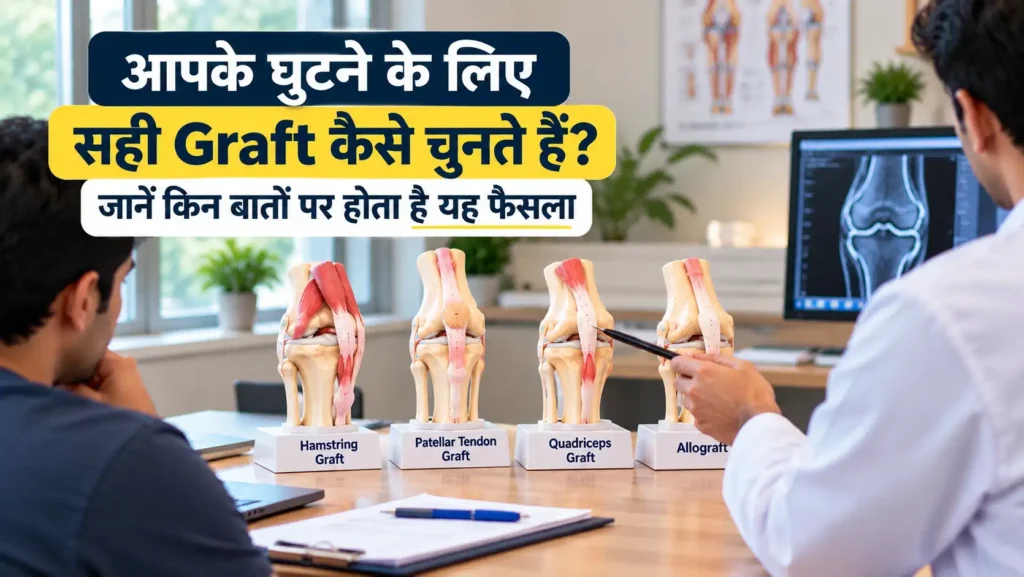
The graft is the new tissue that replaces your torn ligament. There is no single “best” choice. The right pick depends on your age, sport and knee shape. Here is how the common options compare.
| Graft Type | Best Suited For | Recovery Speed | Key Point |
|---|---|---|---|
| Hamstring Tendon | Most active adults | Moderate | Mild early hamstring weakness |
| Patellar Tendon (BTB) | Athletes in pivoting sports | Slower start | Some pain at the front of the knee |
| Quadriceps Tendon | Revision surgery cases | Moderate | Strong graft, larger cut site |
| Allograft (donor tissue) | Older, less active patients | Slower healing | No donor site pain |
Can ACL Reconstruction Be Combined With Meniscus Repair?
Yes, and this happens often. The meniscus is a soft cushion inside your knee. It tears along with the ACL in about half of all major knee injuries.
When both are hurt, we usually fix them in one operation. That means one surgery, one round of anaesthesia and one recovery period, not two. It also means slightly less time off work or training overall, since you are not booking two separate procedures. Get information about meniscus repair done alongside ACL surgery.
What Are the Risks of ACL Reconstruction?
Like any surgery, there are risks. I believe patients deserve to hear them plainly, not glossed over. These include infection, stiffness, graft failure and blood clots. Each is rare with good technique and care.
Three things lower these risks the most. Pick a skilled surgical team. Stick to your physio plan. Avoid hard activity too soon.
Smoking, poor blood sugar control and being significantly overweight can also slow healing and raise infection risk. If any of these apply to you, mention them at your consultation so we can plan around them instead of being surprised later.
Is ACL Reconstruction Painful?
This is the question I hear most. I always answer it honestly. Yes, there is pain, but it is manageable. It does not stay at one level the whole time.
During surgery, you feel nothing due to anaesthesia. For the first two to three days after, most patients feel sore and tight rather than sharp pain. This is well controlled with medicine.
By the end of week one, pain usually drops a lot. What often surprises patients more than pain is the stiffness and swelling. We manage this with ice, elevation and gentle early movement.
ACL Surgery Recovery Timeline: What to Expect
Recovery isn’t one single event. It’s a series of small milestones. Here’s how it typically unfolds.
1. What to Expect During the First Week
The first week is about protecting the knee and controlling swelling. You’ll wear a brace, use crutches and do gentle ankle and knee exercises with your physiotherapist. Rest, ice, and elevation are your main tools here.
2. When Can You Walk After Surgery?
Most patients are able to walk using crutches and a brace within 24 to 48 hours after surgery. Usually, full weight bearing without support returns gradually over a period of 2 to 4 weeks. If a meniscus repair was done, the exact timing will depend on that too.
3. How Long Does the Swelling Last?
Noticeable swelling usually drops within 2 to 3 weeks. Mild puffiness around the knee, especially after activity, can linger for 2 to 3 months. This is normal, not a warning sign.
4. When Can You Start Physiotherapy?
Physio usually starts within the first 3 to 5 days after surgery, not months later, as many patients assume. Early, gentle physio is one of the biggest keys to a smooth recovery.
Your physiotherapy plan moves through clear phases: swelling control, range of motion, strength work, then sport-specific or drill-specific training closer to month nine.
“I have seen the surgery go perfectly, then recovery fail simply because physio was skipped. The operation rebuilds the ligament. Physiotherapy rebuilds the knee,” Dr. Prince often tells his patients at their first check-up.
5. When Can You Return to Normal Activities and Sports?
Light daily tasks, like walking, driving, and desk work, usually resume around 3 to 4 months. Return to running often starts between 4 and 6 months, once strength tests show your leg is ready.
Contact sports and pivoting moves, like football or badminton, along with obstacle training and physical efficiency drills, are usually cleared only after 9 to 12 months. By then, your strength should match your other leg.
6. How Long Does Full Recovery Really Take?
Full ligament healing takes close to a year. You may still feel mostly normal by month four or five. Going back to hard sport, or presenting yourself for a medical board, before month 9 raises your risk of a second tear and of an unfavourable stability assessment.
Think of it in three stages. Protect the knee for the first 6 weeks. Rebuild strength over the next 4 months. Then retrain sport or drill-level movement in the months after that. This is also, broadly, the window most defence aspirants should plan around before their SSB medical, more on that below.
Age, past fitness, and how closely you follow physio all affect your speed here. Two patients with the same tear can heal at very different paces. That is normal.
ACL Reconstruction and SSB Medical Fitness: What Defence Aspirants Need to Know
A large number of the ACL patients I treat in Indore aren’t athletes chasing a comeback season. They are NDA, CDS, AFCAT and Agniveer aspirants who tore their ACL during training, cross-country runs or a football match, and now want a straight answer to one question: does this knee end my chances at the SSB medical?
Here is what I tell them, as honestly as I can.
A History of ACL Surgery Does Not Automatically Mean Permanent Rejection
There is no single, uniform rule that a past ACL reconstruction always results in a permanent unfit. Orthopaedic opinion is genuinely split on this, some surgeons treat any major knee surgery as a red flag for enrolment, others hold that a fully rehabilitated, stable knee should not disqualify a candidate on its own. In practice, the outcome comes down to how your knee performs on the day of your medical, not just what your file says happened months or years ago.
What the board is actually checking for is instability, the same kind the Lachman test looks for. A knee that shows no giving-way, has full range of motion, near-equal strength to the other leg and no swelling has a very different story to tell than one that is still guarded or weak.
How the SSB Medical Process Works
If you disclose a past knee surgery, or it shows up on examination, you will typically go through a Special Medical Board (SMB) evaluation at a military hospital. If the knee is flagged, candidates are usually placed under Temporary Rejection (TR) rather than an outright permanent unfit, which leaves room to demonstrate fitness.
From there, two appeal routes exist if you are still not satisfied with the outcome:
- Appeal Medical Board (AMB): available as a matter of right, usually within 42 days of your last examination.
- Review Medical Board (RMB): a further review, generally requested within a day of the AMB outcome, with the final call resting with the higher medical authority.
Exact timelines and forms are updated from time to time, so always confirm the current process with your recruiting authority or coaching academy before your medical date.
Never Hide a Past Surgery
I say this to every aspirant who sits across from me. Do not conceal an ACL surgery during enrolment. If it is discovered later, even after you have joined, it can mean a permanent ban rather than a temporary setback. A disclosed, well-recovered knee is a far better position than a hidden one that surfaces later.
What Actually Improves Your Chances
- Give the graft time. A knee assessed at 3 months looks nothing like one assessed at 9 to 12 months. Wherever possible, time your medical for after your surgeon has cleared you for full activity, not before.
- Complete your physiotherapy, don’t just attend it. Boards can often tell the difference between a knee that has been strengthened properly and one that has only been rested.
- Get an objective stability and strength assessment before you go. A functional evaluation, including tests like the Lachman test and side-by-side strength comparison, gives you an honest picture of where you stand and, if needed, documentation to support your case at an AMB or RMB.
- Carry your complete surgical and rehab records. Operative notes, physiotherapy progress, and a fitness certificate from your operating surgeon all help the board make an informed call rather than a cautious default one.
If you are an SSB aspirant dealing with an ACL tear, or you have already had reconstruction and want an honest, current assessment of your knee before your medical, that evaluation and the paperwork behind it is something we prepare for candidates regularly at the clinic.
How to Protect Your New ACL
A rebuilt ACL is strong, but it is not invincible. Good habits in the first year lower your risk of a second tear by a wide margin, and they are exactly what a medical board is looking to see reflected in your knee’s stability.
Warm up before sport. Build hip and core strength, not just knee strength. Practice safe landing form under a physio’s eye before you jump back into your sport, or your physical training, at full speed.
What Does the Surgery Cost and Is It Worth It?
Patients often delay care due to cost worry. Price depends on the hospital, the graft used, and whether a meniscus repair is also needed. Check current surgery cost details for a clearer picture before you decide.
Here is what I tell my patients: an unrepaired ACL tear often leads to cartilage damage over time. That can cost far more, and hurt far more, to fix later, and it can quietly close doors like a defence career that a well-managed knee would have kept open. Some patients also qualify for government health schemes, which can lower costs. It is worth asking about this at your first visit. Insurance coverage varies too, so bring your policy details to that first meeting. A little planning upfront saves a lot of confusion once surgery is scheduled.
Final Thoughts
ACL reconstruction can feel like a lot to take in at first. But it is one of the most well-studied, predictable surgeries in orthopaedics today. With the right plan and honest work in physio, most patients get back to what they love, from daily walks to competitive sport, and for many of my patients, to the SSB medical they have been preparing years for.
If you’re dealing with knee instability or a suspected ACL injury, don’t wait for it to “get better on its own”, and don’t wait until the week before your medical to find out where your knee actually stands. Book a consultation through our sports injury treatment page. Or reach out via our contact page to discuss your case, including a pre-SSB fitness evaluation. For rehab support after surgery, our physiotherapy and rehabilitation team works closely with every surgical patient. If a meniscus issue is part of your diagnosis, learn more on our meniscus tear treatment page.
Your knee’s stability is worth getting right the first time, whether you’re chasing a personal best or a place in the armed forces.